Duodenal Resurfacing, Liners and the Next Endoscopic Devices
A device built on one careful sentence about gastric bypass, read clause by clause, and what the sources leave unsaid about it.
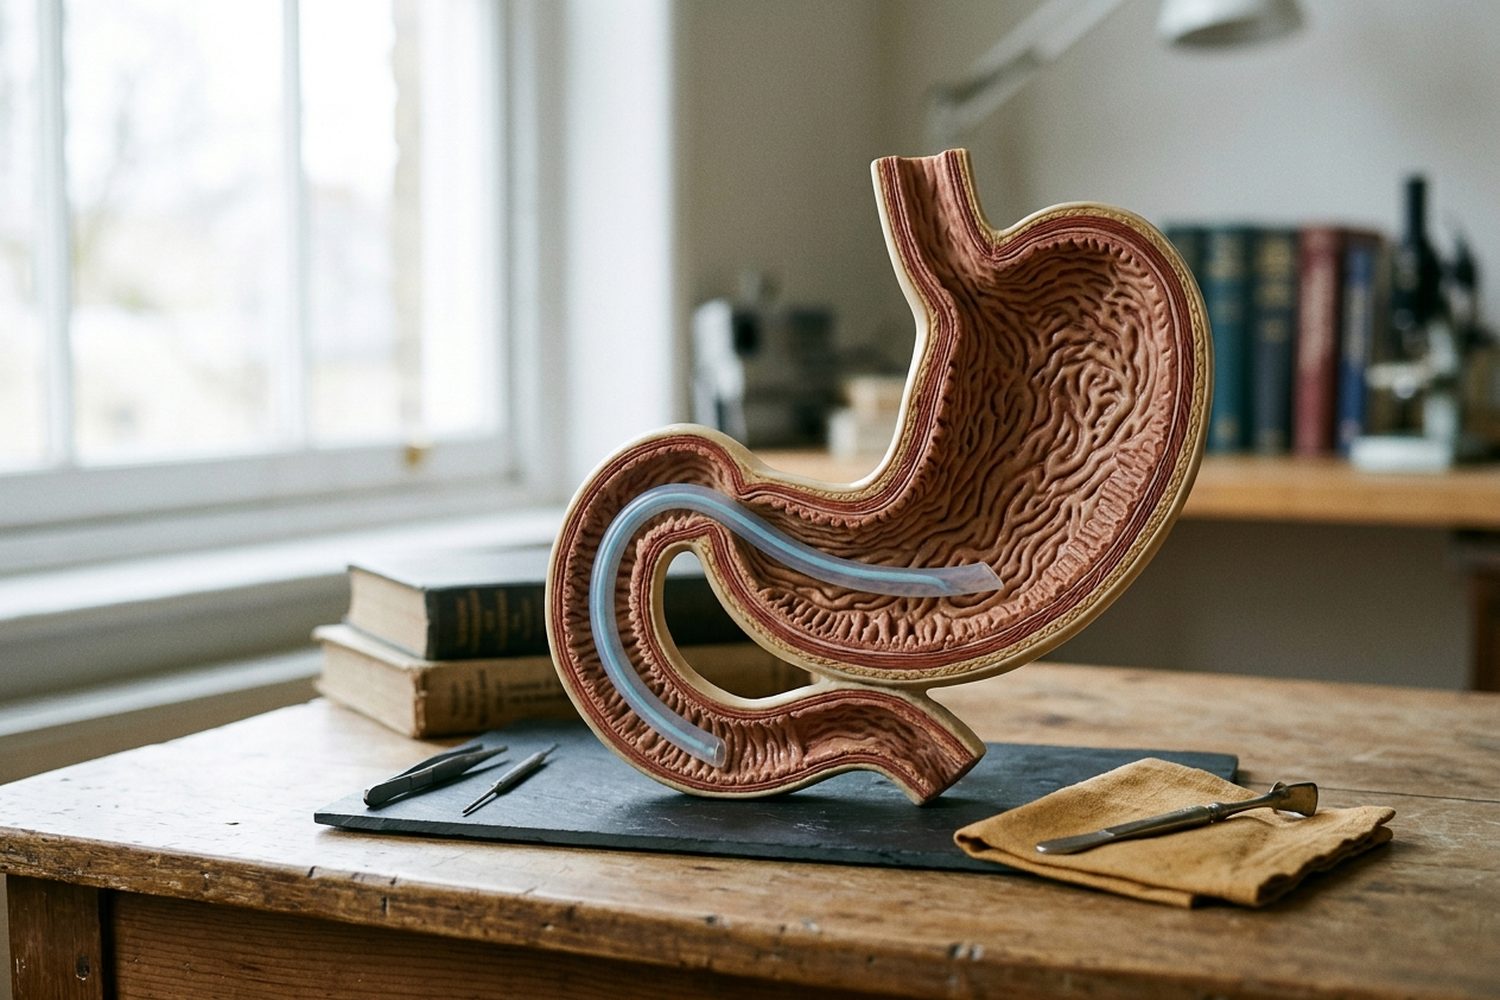
The way the duodenal device business works is that surgeons produce a result they cannot fully explain, and then engineers try to sell the unexplained part separately, without the surgery. Gastric bypass reroutes food past the duodenum (the first stretch of the small intestine), and its diabetes benefits seem to outlast its weight loss. So a lot of clever people have asked whether you could get the duodenum part from the inside, through an endoscope, with no incisions. That family of ideas includes liners, duodenal mucosal resurfacing (DMR), aspiration therapy and a few others.
If you got here by typing endobarrier into a search box, here is the plain answer as far as my sources go. EndoBarrier is the best-known name for the liner idea, and the evidence in front of me does not settle its current status, its regulatory approval or its trial results. I am not going to invent them. (This is a website, not a press release.) What the sources do settle is the reasoning these devices rest on, and the fact that a formal comparison of “all currently available FDA-approved” endoscopic therapies covered balloons and stitched stomachs, not intestinal liners.
The sentence EndoBarrier and resurfacing are built on
Here is the sentence, from the American College of Surgeons’ write-up of a Mayo Clinic study on gastric bypass and diabetes: “Even RYGB patients who regained 100% or more of their surgically-lost weight still maintained T2DM remission in approximately 60% of cases, supporting a weight-independent metabolic benefit from duodenal bypass.”
That is a careful sentence, written by people who knew it would be quoted. I am going to read it like a contract, because that is basically the only skill I have. (My job consists mostly of reading other people’s sentences more slowly than they intended.)
Reading it one clause at a time
“Even.” This word announces that the sentence is about to break an assumption. The normal assumption is that diabetes improves after surgery because the person gets lighter. “Even” tells you the authors found people for whom that link snapped, and the diabetes stayed improved anyway.
“RYGB patients.” Roux-en-Y gastric bypass, specifically. Not sleeve. This matters, because the same Mayo work found that 75% of bypass patients kept remission at five years despite weight regain, versus 34.8% of sleeve patients, with odds of diabetes coming back 5.5 times higher after the sleeve. A sleeve shrinks the stomach and leaves the duodenum in the path of food. A bypass routes food around it. Hold that thought.
“Who regained 100% or more of their surgically-lost weight.” Read literally, this is a group of people who had a major operation to lose weight and then ended up, on the scale, where they started or heavier. I was going to say they got none of the benefit of the surgery. That is wrong, and the precise version is stranger: they got none of the benefit they signed up for, and most of them kept a different benefit that nobody ordered separately.
“Still maintained T2DM remission.” Remission, which is a status that can end, rather than a cure. The sentence does not promise forever. It reports what was true at the time of measurement.
“In approximately 60% of cases.” So about six in ten people whose operation failed by its own headline metric had diabetes that stayed in remission. It is not nothing. It is, to put it gently, a fairly large number to find living inside a group defined by failure.
“Supporting.” Not proving. Observational follow-up of surgical patients can support a theory, and the authors chose the verb that says exactly that much. (Researchers pick verbs the way lawyers do, which is to say expensively.)
“A weight-independent metabolic benefit.” Here is the plain version: when food skips the first part of the intestine, blood sugar seems to behave better, whether or not the person stays thinner. The official name for that is a weight-independent metabolic benefit.
“From duodenal bypass.” This is the clause the device industry reads. Notice it does not say “from gastric bypass.” It assigns the credit to the duodenum. Somewhere an engineer read this and said to a colleague, “Hey, what if we just sold the duodenum part?” It is sort of like hearing a band’s big hit, deciding the drum solo was the good bit, and booking a tour of just the drum solo.
What the duodenum part looks like without surgery
If the benefit comes from food not touching the duodenal wall, there are roughly two endoscopic ways to chase it. You can put something between the food and the wall, which is the liner approach that EndoBarrier is known for. Or you can change the wall itself, which is what “resurfacing” in DMR says it does. Aspiration therapy is a different idea (its name carries more information than my sources do, so I will let the name speak for itself).
To be fair, the logic is reasonable. But notice the gap. The ACS sentence is about a permanent surgical rerouting. A liner or a resurfacing is a guess about which ingredient of that rerouting does the work, and whether a temporary or partial version keeps the effect. The sentence does not say. Neither do my sources.
There is also a selection question the sentence quietly raises. Remission after bypass is not uniform: reviews list shorter diabetes duration, lower baseline HbA1c and preserved beta-cell function as predictors, and remission is associated with not having been on insulin before surgery. For instance, when researchers applied a surgical scoring tool to endoscopic sleeve gastroplasty patients, remission ran 60% in the mild group, 45.5% in the moderate group and 0% in the severe group. So any duodenal device would presumably face the same sorting. Whether it does, for these devices, is not settled by anything I have.
Where the endoscopic options actually stand
Look, here is what the sources do pin down. A network meta-analysis of randomized trials searched MEDLINE, EMBASE and Cochrane CENTRAL for balloon studies from inception and for ESG studies from 2013 until May 2023. It concluded that at the time of balloon removal, “all currently available FDA-approved endoscopic bariatric therapies were associated with statistically significantly higher percentage total weight loss than control interventions.” ESG ranked highest at 12 months (P-score 0.899), ahead of the Spatz3 and Orbera balloons.
Now read that literally too. “All currently available FDA-approved” is a claim about a complete list, and the search terms tell you what the list was: balloons, adjustable balloons, ESG. Liners and resurfacing are not on it. Why not? Maybe they were not approved, maybe not available, maybe they lacked trials that fit the criteria. The sentence does not choose, and I cannot either. It must be a lonely thing, being a device whose most quotable evidence is a sentence about somebody else’s operation.
The things that are on the list have their own articles on this site, so briefly: in the MERIT trial, ESG produced 13.6% total body weight loss at 52 weeks versus 0.8% with lifestyle changes, and balloon weight loss, per one review, “is not sustained long-term after device removal.” A systematic review also found that adding liraglutide to endoscopic therapy matched the net weight loss of surgery, defined as nadir minus regained weight (a comparison that politely subtracts surgery’s worst years before keeping score).
Why the duodenum story keeps pointing back to surgery
The strongest evidence for the duodenum theory comes from comparing operations with each other, not from devices. In the Oseberg randomized trial, gastric bypass reached 63% diabetes remission at five years versus 30% for sleeve gastrectomy. Other work found bypass and duodenal switch carried lower risks of diabetes recurrence than the sleeve. Both of the winners reroute food around the duodenum. The sleeve does not.
That is the whole pitch for the next generation of endoscopic devices, I guess: take the clause “from duodenal bypass,” and try to deliver it without the bypass. It is an elegant sort of thing to attempt. Whether it works is a question for trials that do not appear in my sources.
The network meta-analysis that defined the current shelf identified 821 citations, and 8 made it into the quantitative analysis.
Sources
- Weight Loss Effect of GLP-1 RAs With Endoscopic Bariatric Therapy and Bariatric Surgeries
- Gastric Bypass Improves Long-Term Diabetes Remission, Even After Weight Recurrence | ACS
- Continued Diabetes Remission Despite Weight Recurrence: Gastric Bypass Long-Term Metabolic Benefit.
- Comparative effectiveness of balloons, adjustable balloons, and endoscopic sleeve gastroplasty: a network meta-analysis of randomized trials
- Applicability of individualized metabolic surgery score for prediction of diabetes remission after endoscopic sleeve gastroplasty
- Beyond Initial Resolution: Predictors of Recurrence of Obesity-related Medical Conditions after Metabolic and Bariatric Surgery
- Endobariatrics: well past infancy and maturing rapidly
- Lifestyle Modification and Bariatric Surgery in Type 2 Diabetes Remission : Short title: Diabetes Remission Strategies in T2DM
- Advances in Metabolic Bariatric Surgeries and Endoscopic Therapies: A Comprehensive Narrative Review of Diabetes Remission Outcomes
- Bariatric Surgery and Type 2 Diabetes Remission and Relapse: Mechanisms, Predictive Factors, and Postoperative Management — a Review Article | Ciesielska | Clinical Diabetology
- Endoscopic sleeve gastroplasty for treatment of class 1 and 2 obesity (MERIT): a prospective, multicentre, randomised trial
- Effect of gastric bypass versus sleeve gastrectomy on the remission of type 2 diabetes, weight loss, and cardiovascular risk factors at 5 years (Oseberg): secondary outcomes of a single-centre, triple-blind, randomised controlled trial.
Bariatric Alt explains published research. It is not medical advice, and it never recommends a surgeon, a clinic, a dose or a product. Talk to a clinician about which option fits you.